


本文转载于重庆医学2025年5月第54卷第5期,不代表本网站赞同其观点和对其真实性负责,我们只作于阅读分享,非商业用途,如若侵权,请告知删除。
王利娇,何小兰
(温州医科大学附属第一医院创面修复中心,浙江温州 325035)
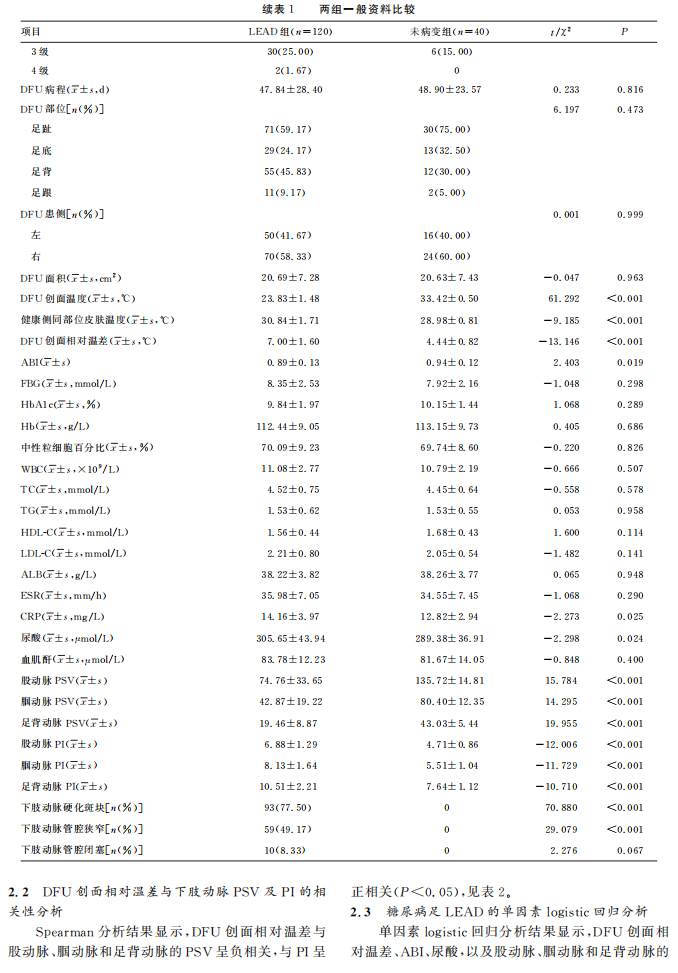
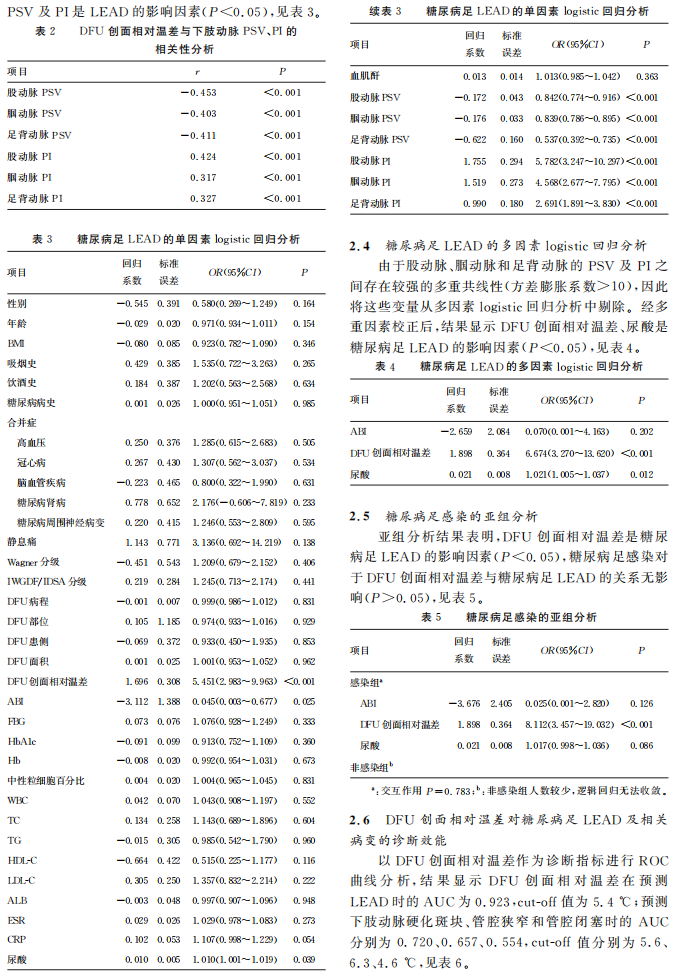
[摘要] 目的 探讨基于红外热成像的皮肤温度监测对糖尿病足患者下肢动脉病变(LEAD)的诊断价值。方法 选取2023年3月至2024年12月该院收治的160例糖尿病足患者为研究对象,根据彩色多普勒超声诊断结果分为 LEAD组(n=120)和未病变组(n=40)。Spearman分析红外热成像的糖尿病足溃疡(DFU)创面相对温差与下肢动脉血管内径及血流量之间的相关性,逐步logistic回归分析 LEAD的影响因素并按照是否感染进行亚组分析,受试者工作特征(ROC)曲线分析用于评估 DFU 创面相对温差对 LEAD 及下肢动脉硬化斑块、管腔狭窄和腔闭塞的诊断效能。结果 两组不同 DFU 创面温度、健康侧同部位皮肤温度、DFU 创面相对温差、踝肱指数(ABI)、C反应蛋白(CRP)、尿酸和股动脉、腘动脉、足背动脉血流峰值流速(PSV)、搏动指数(PI)水平及下肢动脉硬化斑块、下肢动脉管腔狭窄比例比较,差异有统计学意义(P<0.05)。Spearman分析结果显示,DFU 创面相对温差与股动脉、腘动脉和足背动脉的 PSV 呈负相关,与 PI呈正相关(P<0.05)。单因素logistic回归分析显示,DFU 创面相对温差、ABI、尿酸,以及股动脉、腘动脉和足背动脉的 PSV 及 PI是LEAD的影响因素(P <0.05)。多 因 素logistic回 归 分 析 结 果 显 示,DFU 创 面 相 对 温 差、尿 酸 是 糖 尿 病 足LEAD的影响因素(P<0.05)。亚组分析结果表明,DFU 创面相对温差是糖尿病足 LEAD 的影响因素(P<0.05),糖尿病足感染对于 DFU 创面相对温差与糖尿病足 LEAD的关系无响(P>0.05)。DFU 创面相对温差在预测 LEAD时的曲线下面积(AUC)为0.923,cut-off值为5.4 ℃;预测下肢动脉硬化斑块、管腔狭窄及管腔闭塞时的 AUC分别为0.720、0.657和0.554,cut-off值分别为5.6、6.3、4.6℃。结论红外热成像的 DFU创面相对温差可有效诊断 LEAD。
[关键词] 红外热成像;糖尿病足;下肢动脉病变;创面相对温差;诊断价值[中图法分类号] R587.2[文献标识码] A[文章编号] 1671-8348(2025)05-1085-07
Diagnostic value of infrared thermography-based skin temperature monitoringfor lower extremity arterial disease in patients with diabetic foot
WANG Lijiao,HE Xiaolan
(Wound Repair Center ,the First Affiliated Hospital of Wenzhou Medical University, Wenzhou,Zhejiang 325035,China)
[Abstract]
Objective To investigates the diagnostic value of infrared thermography-based skin temper-ature monitoring for lower extremity arterial disease (LEAD) in patients with diabetic foot. Methods A totalof 160 patients with diabetic foot admitted to the hospital from March 2023 to December 2024 were selected asthe research subjects and divided into the LEAD group (n=120) and the non-lesion group (n=40) based onthe diagnostic results of color Doppler ultrasound. Spearman analysis was used to evaluate the correlation be-tween the relative temperature of diabetic foot ulcer (DFU) wounds measured by infrared thermography andthe diameter and blood flow of lower limb arteries, Stepwise logistic regression analysis was performed to i-dentify the influencing factors of LEAD and subgroup analysis was conducted based on the presence or absenceof infection. Receiver operating characteristic (ROC) curve analysis was used to assess the diagnostic efficacyof DFU wound relative temperature for LEAD and lower limb arterial atherosclerotic plaques,lumen stenosis.and lumen occlusion. Results There were statistically significant differences between the two groups in DFUwound temperature,skin temperature at the same site on the healthy side. DFU wound relative temperature.ankle brachial index (ABD,C-reactive protein (CRP), uric acid, and the peak velocity (PSV) and pulsatility index (PI) levels of the femoral artery. popliteal artery,and dorsalis pedis artery,as well as the proportions oflower limb arterial atherosclerotic plaques and lumen stenosis (P<0. 05). Spearman analysis showed that therelative temperature of DFU wounds was negatively correlated with PSV of the femoral artery.popliteal arter-y,and dorsalis pedis artery,and positively correlated with PI (P<0. 05). Univariate logistic regression analysis indicated that ABI.DFU wound relative temperature, uric acid,and the PSV and PI of the femoral artery.popliteal artery.and dorsalis pedis artery were influencing factors for LEAD (P<0. 05). Multivariate logisticregression analysis revealed that DFU wound relative temperature and uric acid were influencing factors forLEAD in diabetic foot (P <0. 05). Subgroup analysis showed that DFU wound relative temperature was an in-fluencing factor for LEAD in diabetic foot (P <0. 05),and there was no interaction between diabetic foot infection and the relationship between DFU wound relative temperature and LEAD in diabetic foot (P>0. 05).The area under the curve (AUC) for predicting LEAD using DFU wound relative temperature was 0.923,withthe cut-off temperature being 5.4 °C. The AUCs for predicting lower limb arterial atherosclerotic plaques. lumenstenosis,and lumen occlusion were 0. 720,0. 657 ,and 0. 554, respectively, with the cut-off temperatures being5. 6.6. 3,and 4. 6 °C.respectively.
Conclusion DFU wound surface relative temperature of infrared thermography can effectively diagnose LEAD in diabetic foot.
Key words: infrared thermography;diabetic foot; lower extremity arterial disease; wound surface relative temperature; diagnostic value
本文转载于重庆医学2025年5月第54卷第5期,不代表本网站赞同其观点和对其真实性负责,我们只作于阅读分享,非商业用途,如若侵权,请告知删除。
